
Deep Reinforcement Learning for Efficient and Fair Allocation of Healthcare Resources
Proceedings of the Thirty-Fourth International Joint Conference on Artificial Intelligence. AI and Social Good. Pages 9790-9798.
https://doi.org/10.24963/ijcai.2025/1088
Keywords
- AI Ethics, Trust, Fairness: General
- Multidisciplinary Topics and Applications: General
- Planning and Scheduling: General
Abstract
The scarcity of health care resources, such as ventilators, often leads to the unavoidable consequence of rationing, particularly during public health emergencies or in resource-constrained settings like pandemics. The absence of a universally accepted standard for resource allocation protocols results in governments relying on varying criteria and heuristic-based approaches, often yielding suboptimal and inequitable outcomes. This study addresses the societal challenge of fair and effective critical care resource allocation by leveraging deep reinforcement learning to optimize policy decisions. We propose a transformer-based deep Q-network that integrates individual patient disease progression and interaction effects among patients to enhance allocation decisions. Our method aims to improve both fairness and overall patient outcomes. Experiments using metrics such as normalized survival rates and interracial allocation rate differences demonstrate that our approach significantly reduces excess deaths and achieves more equitable resource allocation compared to severity- and comorbidity-based protocols currently in use. Our findings highlight the potential of deep reinforcement learning to address critical health care challenges.
- [Ahmad et al., 2020] Muhammad Aurangzeb Ahmad, Arpit Patel, Carly Eckert, Vikas Kumar, and Ankur Teredesai. Fairness in machine learning for healthcare. In Proceed- ings of the 26th ACM SIGKDD International Conference on Knowledge Discovery & Data Mining, pages 3529- 3530, 2020.
- [Ashana et al., 2021] Deepshikha Charan Ashana, George L Anesi, Vincent X Liu, Gabriel J Escobar, Christo- pher Chesley, Nwamaka D Eneanya, Gary E Weissman, William Dwight Miller, Michael O Harhay, and Scott D Halpern. Equitably allocating resources during crises: racial differences in mortality prediction models. Amer- ican journal of respiratory and critical care medicine, 204(2):178-186, 2021.
- [Awasthi et al., 2022] Raghav Awasthi, Keerat Kaur Guliani, Saif Ahmad Khan, Aniket Vashishtha, Mehrab Singh Gill, Arshita Bhatt, Aditya Nagori, Aniket Gupta, Pon- nurangam Kumaraguru, and Tavpritesh Sethi. Vacsim: Learning effective strategies for covid-19 vaccine distri- bution using reinforcement learning. Intelligence-Based Medicine, 6:100060, 2022.
- [Bastani et al., 2021] Hamsa Bastani, Kimon Drakopoulos, Vishal Gupta, Ioannis Vlachogiannis, Christos Had- jichristodoulou, Pagona Lagiou, Gkikas Magiorkinis, Dimitrios Paraskevis, and Sotirios Tsiodras. Efficient and targeted covid-19 border testing via reinforcement learn- ing. Nature, 599(7883):108-113, 2021.
- [Bednarski et al., 2021] Bryan P Bednarski, Akash Deep Singh, and William M Jones. On collaborative rein- forcement learning to optimize the redistribution of crit- ical medical supplies throughout the covid-19 pandemic. Journal of the American Medical Informatics Association, 28(4):874-878, 2021.
- [Bhavani et al., 2021] Sivasubramanium V Bhavani, Yuan Luo, William D Miller, Lazaro N Sanchez-Pinto, Xuan Han, Chengsheng Mao, Burhaneddin Sandıkc ¸ı, Monica E Peek, Craig M Coopersmith, Kelly N Michelson, et al. Simulation of ventilator allocation in critically ill patients with covid-19. American journal of respiratory and criti- cal care medicine, 204(10):1224-1227, 2021.
- [Biddison et al., 2019] E Lee Daugherty Biddison, Ruth Faden, Howard S Gwon, Darren P Mareiniss, Alan C Regenberg, Monica Schoch-Spana, Jack Schwartz, and Eric S Toner. Too many patients. . . a framework to guide statewide allocation of scarce mechanical ventilation dur- ing disasters. Chest, 155(4):848-854, 2019.
- [Bird et al., 2020] Sarah Bird, Miro Dudík, Richard Edgar, Brandon Horn, Roman Lutz, Vanessa Milan, Mehrnoosh Sameki, Hanna Wallach, and Kathleen Walker. Fairlearn: A toolkit for assessing and improving fairness in ai. Mi- crosoft, Tech. Rep. MSR-TR-2020-32, 2020.
- [Chen et al., 2008] Esther H Chen, Frances S Shofer, An- thony J Dean, Judd E Hollander, William G Baxt, Jen- nifer L Robey, Keara L Sease, and Angela M Mills. Gen- der disparity in analgesic treatment of emergency depart- ment patients with acute abdominal pain. Academic Emer- gency Medicine, 15(5):414-418, 2008.
- [Cimpean et al., 2023] Alexandra Cimpean, Timothy Ver- straeten, Lander Willem, Niel Hens, Ann Nowé, and Pieter Libin. Evaluating covid-19 vaccine allocation poli- cies using bayesian m-top exploration. arXiv preprint arXiv:2301.12822, 2023.
- [Dresser, 1992] Rebecca Dresser. Wanted single, white male for medical research. The Hastings Center Report, 22(1):24-29, 1992.
- [Emanuel and Wertheimer, 2006] Ezekiel J Emanuel and Alan Wertheimer. Who should get influenza vaccine when not all can? Science, 312(5775):854-855, 2006.
- [Emanuel et al., 2020] Ezekiel J Emanuel, Govind Persad, Ross Upshur, Beatriz Thome, Michael Parker, Aaron Glickman, Cathy Zhang, Connor Boyle, Maxwell Smith, and James P Phillips. Fair allocation of scarce medical resources in the time of covid-19, 2020.
- [Gostin et al., 2012] Lawrence O Gostin, Kristin Viswanathan, Bruce M Altevogt, Dan Hanfling, et al. Crisis standards of care: a systems framework for catas- trophic disaster response: Volume 1: Introduction and CSC framework, volume 3. National Academies Press, 2012.
- [Grand-Clément et al., 2021] Julien Grand-Clément, Carri W. Chan, Vineet Goyal, and Elizabeth Chuang. In- terpretable machine learning for resource allocation with application to ventilator triage. CoRR, abs/2110.10994, 2021.
- [Levine et al., 2020] Sergey Levine, Aviral Kumar, George Tucker, and Justin Fu. Offline reinforcement learning: Tu- torial, review, and perspectives on open problems. arXiv preprint arXiv:2005.01643, 2020.
- [Li et al., 2022] Yikuan Li, Hanyin Wang, and Yuan Luo. Improving fairness in the prediction of heart failure length of stay and mortality by integrating social determinants of health. Circulation: Heart Failure, 15(11):e009473, 2022.
- [Liu et al., 2018] Lydia T Liu, Sarah Dean, Esther Rolf, Max Simchowitz, and Moritz Hardt. Delayed impact of fair ma- chine learning. In International Conference on Machine Learning, pages 3150-3158. PMLR, 2018. IJCAI
- [Mehrabi et al., 2021] Ninareh Mehrabi, Fred Morstatter, Nripsuta Saxena, Kristina Lerman, and Aram Galstyan. A survey on bias and fairness in machine learning. ACM Computing Surveys (CSUR), 54(6):1-35, 2021.
- [Mnih et al., 2013] Volodymyr Mnih, Koray Kavukcuoglu, David Silver, Alex Graves, Ioannis Antonoglou, Daan Wierstra, and Martin Riedmiller. Playing atari with deep reinforcement learning. arXiv preprint arXiv:1312.5602, 2013.
- [Persad et al., 2009] Govind Persad, Alan Wertheimer, and Ezekiel J Emanuel. Principles for allocation of scarce medical interventions. The lancet, 373(9661):423-431, 2009.
- [Pfohl et al., 2021] Stephen R Pfohl, Agata Foryciarz, and Nigam H Shah. An empirical characterization of fair machine learning for clinical risk prediction. Journal of biomedical informatics, 113:103621, 2021.
- [Piscitello et al., 2020] Gina M Piscitello, Esha M Kapa- nia, William D Miller, Juan C Rojas, Mark Siegler, and William F Parker. Variation in ventilator allocation guide- lines by us state during the coronavirus disease 2019 pandemic: a systematic review. JAMA network open, 3(6):e2012606-e2012606, 2020.
- [Rajkomar et al., 2018] Alvin Rajkomar, Michaela Hardt, Michael D Howell, Greg Corrado, and Marshall H Chin. Ensuring fairness in machine learning to advance health equity. Annals of internal medicine, 169(12):866-872, 2018.
- [Raschke et al., 2021] Robert A Raschke, Sumit Agarwal, Pooja Rangan, C William Heise, and Steven C Curry. Dis- criminant accuracy of the sofa score for determining the probable mortality of patients with covid-19 pneumonia requiring mechanical ventilation. Jama, 325(14):1469- 1470, 2021.
- [Rey et al., 2023] David Rey, Ahmed W Hammad, and Meead Saberi. Vaccine allocation policy optimization and budget sharing mechanism using reinforcement learning. Omega, 115:102783, 2023.
- [Tamayo-Sarver et al., 2003] Joshua H Tamayo-Sarver, Su- san W Hinze, Rita K Cydulka, and David W Baker. Racial and ethnic disparities in emergency department analgesic prescription. American journal of public health, 93(12):2067-2073, 2003.
- [Truog et al., 2006] Robert D Truog, Dan W Brock, Deb- orah J Cook, Marion Danis, John M Luce, Gordon D Rubenfeld, Mitchell M Levy, et al. Rationing in the in- tensive care unit. Critical care medicine, 34(4):958-963, 2006.
- [Van Hasselt et al., 2016] Hado Van Hasselt, Arthur Guez, and David Silver. Deep reinforcement learning with dou- ble q-learning. In Proceedings of the AAAI conference on artificial intelligence, volume 30, 2016.
- [Vaswani et al., 2017] Ashish Vaswani, Noam Shazeer, Niki Parmar, Jakob Uszkoreit, Llion Jones, Aidan N Gomez, Łukasz Kaiser, and Illia Polosukhin. Attention is all you need. Advances in neural information processing systems, 30, 2017.
- [VEN, 2015] Ventilator allocation guidelines, Nov 2015.
- [Wang et al., 2022] Hanyin Wang, Yikuan Li, Andrew Naidech, and Yuan Luo. Comparison between machine learning methods for mortality prediction for sepsis pa- tients with different social determinants. BMC Medical Informatics and Decision Making, 22(2):1-13, 2022.
- [Yu et al., 2021] Chao Yu, Jiming Liu, Shamim Nemati, and Guosheng Yin. Reinforcement learning in healthcare: A survey. ACM Computing Surveys (CSUR), 55(1):1-36, 2021.
- [Zong and Luo, 2022] Kai Zong and Cuicui Luo. Reinforce- ment learning based framework for covid-19 resource allo- cation. Computers & Industrial Engineering, 167:107960, 2022.
References were extracted automatically from the PDF and may contain errors.
Full text extracted automatically from the PDF; figures, tables and equations may differ. The PDF is the version of record.
1 Introduction
The Institute of Medicine (IOM) defines Crisis Standards of Care as "a substantial change in usual health care operations and the level of care it is possible to deliver, which is made necessary by a pervasive (e.g., pandemic influenza) or catastrophic (e.g., earthquake) disaster" [Gostin et al., 2012]. These guidelines recognize that pandemics can strain health systems into an absolute scarcity of health care resources and could result in the unavoidable consequence of rationing.
Following the IOM framework, state governments throughout the U.S. have developed allocation protocols for critical care resources during the pandemic [Piscitello et al., 2020]. Consistent with the broad consensus of ethicists and stakeholders [Emanuel et al., 2020], these protocols aim to triage patients via a pre-specified and transparent policy.
Societal Challenges: Despite adhering to a general framework, critical details of these protocols vary widely across the U.S. [Piscitello et al., 2020]. The protocols also differ in whether they prioritize younger patients or those without preexisting medical conditions. For example, the SOFA protocol (used in New York [VEN, 2015]) focuses on maximizing short-term survival and does not consider age or pre-existing conditions; multiprinciple protocols (used in Maryland and Pennsylvania) give preference to younger patients and those without comorbidities [Biddison et al., 2019]. However, all these protocols assign a static priority score, lacking the flexibility to account for the severity of scarcity and the specific patient pool they are competing against, which leaves room for improvement in patient outcomes.
Beyond the lack of a universally accepted protocol, there is also a pressing societal challenge regarding health equity in resource allocation. Empirical assessments indicate that existing allocation protocols disproportionately disadvantaged Black patients, who were significantly less likely to receive ventilators [Bhavani et al., 2021]. Furthermore, the SOFA score, widely used in triage decisions, has been shown to be only moderately effective in predicting mortality for mechanically ventilated patients [Raschke et al., 2021]. Additionally, evidence suggests that SOFA scores may inadvertently assign higher severity scores to Black patients, which could lead to their lower prioritization for life-saving interventions. [Ashana et al., 2021] These disparities highlight the urgent need to improve both the effectiveness and fairness of allocation protocols to ensure that critical resources are allocated efficiently and equitably among all patients.
Multidisciplinary Collaboration Given that resource allocation decisions are made sequentially and must adapt to evolving patient conditions, reinforcement learning (RL) provides a natural framework for optimizing allocation protocols. RL can leverage large-scale patient data and has the potential to learn optimal allocation strategies that maximize lives saved while ensuring fairness across demographic groups. Developing such an approach requires a multidisciplinary effort that brings together health informaticians and AI researchers. By integrating expertise in clinical decisionmaking, health data science, and AI, we can design an RL
model tailored to the complexities of real-world health crises.
In this study, we investigate the use of RL for optimizing critical care resource allocation policies. Our goal is to develop an adaptive, data-driven allocation policy that maximizes survival rates while promoting fairness in rationing across different racial populations. Our main contributions are summarized as follows:
- We formulate fair health care resource allocation as a multi-objective deep reinforcement learning problem, by integrating the utilitarian and egalitarian objectives into the RL rewards.
- We propose a Transformer-based parametrization of the deep Q-network that significantly reduces the complexity of the classical deep-Q network while making allocation decisions based on individual patient disease progression and interactions among patients.
- We apply our approach to a large, diverse, multi-hospital real-world clinical datasets. Experiments show that our approach leads to fair allocation of critical care resources among different races, while maintaining the overall utility with respect to patient survival.
2 RelatedWork
Health care resource scarcity, especially during pandemics and in intensive care settings, requires decision strategies that balance outcomes, equity, and crisis management [Emanuel and Wertheimer, 2006; Truog et al., 2006; Persad et al.,
2009]. Despite these goals, implicit and explicit discrimination has long permeated healthcare, resulting in numerous instances of biased outcomes [Dresser, 1992; Tamayo-Sarver et al., 2003; Chen et al., 2008].
RL, given its inherent capacity for goal-oriented learning and sequential decision-making, holds promise for developing optimized allocation strategies. However, like other machine learning methods, RL can inadvertently reinforce disparities by favoring majority groups and failing to incorporate fairness objectives [Mehrabi et al., 2021]. Indeed, RL may further exacerbate inequities across patient populations if fairness considerations are neglected [Liu et al., 2018; Ahmad et al., 2020; Rajkomar et al., 2018; Pfohl et al., 2021; Wang et al., 2022; Li et al., 2022].
Existing work on resource allocation has primarily focused on one-time or rollout-based distribution, such as vaccine allocation [Awasthi et al., 2022; Rey et al., 2023; Cimpean et al., 2023], often using multi-armed bandit approaches. These methods, however, are ill-suited for complex scenarios requiring repeated, daily allocation decisions.
RL has also been applied to simulate pandemic trajectories, guide lockdown strategies [Zong and Luo, 2022], project ventilator needs [Bednarski et al., 2021], and allocate PCR tests for COVID-19 screening [Bastani et al., 2021]. For a comprehensive summary of RL applications in healthcare, see the survey by [Yu et al., 2021]. Nonetheless, many of these efforts prioritize efficiency over long-term fairness, leaving critical gaps in addressing disparities in high-stakes resource allocation.
3 ProblemFormulation
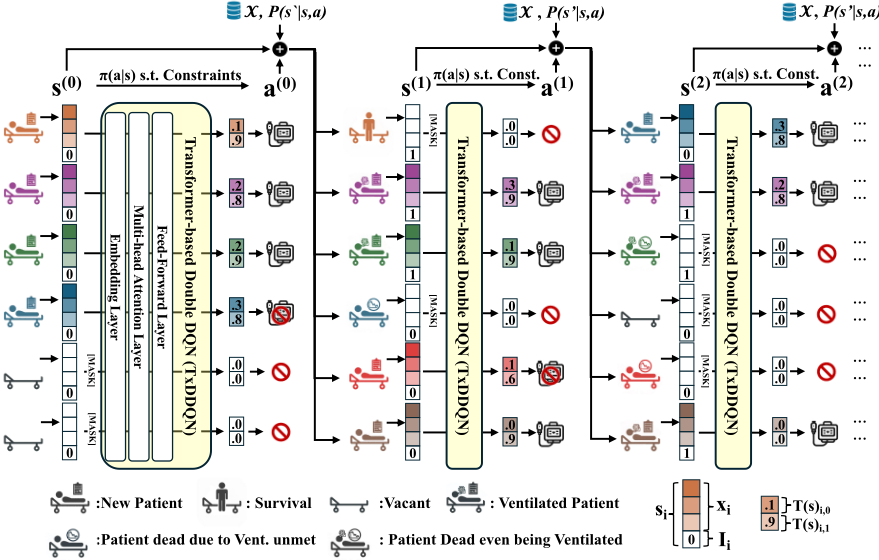
We formulate the ventilator allocation problem as a day-today sequential decision problem, as illustrated in Figure 1. Our objective is to optimize the triage protocol regarding who should receive health resources under scarcity, with the goal of saving more lives during a health crisis. This optimization by no means influences physicians' medical decisions regarding whether a patient should be ventilated or not. Therefore, in our formulation and experiments, all patients are prescribed ventilation by physicians but might not receive one due to resource limitation.
3.1 State Space
The state space S describes the current clinical conditions of all patients in the hospital, as well as their ventilation status. Each state is represented by s = [x1, x2, · · · , xN, I1, I2, · · · , IN] ∈ S ⊆ RkN+N , where xi ∈ [0, 1]k ⊆ Rk denotes the current medical condition of the patient on bed i, and indicator Ii ∈ {0, 1} denotes whether the bed i has been ventilated. Apart from normal medical conditions of patients, we consider three special conditions: Survived, Dead, and Vacant, corresponding to the cases where the patient in this bed is recovered or dead after ventilation, as well as currently no patient in this bed. They act as terminators for patients or separators between patients in the same bed. Such designs separate different patients on the same bed explicitly, so that the tasks of learning the progression of medical conditions given ventilation and the task of recognizing the end of each patient can be decoupled. The intensive care units have up to N beds. Here we only consider ventilator scarcity, but bed scarcity can be analogously modeled. In the following, we give a rigorous formulation of the RL model for both cases of without and with the consideration of the fairness in distributing ventilators.
With fairness in consideration, we further record the cumulative numbers of total and ventilated patients of different ethnoracial groups in the state vector, denoted by nk, mk ∈ R respectively, where k ∈ {B,W, A,H} denotes 4 ethnoracial group in the dataset: non-Hispanic Black, non-Hispanic White, non-Hispanic Asian, Hispanic. Thus, each state s = [x1, · · · , xN, I1, · · · , IN, nB, nW, nA, nH,mB,mW,mA, mH] ∈ S ⊆ RkN+N+8 describes the medical and ventilation status of all current patients, as well as the number of cumulative total and ventilated patients of different groups.
3.2 Action Space
For both cases, the action space A is a discrete space denoting whether each bed is on ventilation or not. Let us use 1 to denote ventilate and 0 otherwise, so the action space A ⊆ {0, 1}N . Note that we have two constraints on actions:
- Capacity Constraint: A ⊆ {a ∈ {0, 1}N : ∑Ni=1 ai ≤ C}, where C is the ventilator capacity of the hospital.
- Withdrawal Constraint (optional): a patient who has been ventilated must not be withdrawn until they no longer need it or are discharged.: A ⊆ {a ∈ {0, 1}N : ai = 1 if Ii = 1, i = 1, 2, · · · ,N}, where Ii in the state information denotes whether current patient on bed i has been ventilated before. We apply this constraint
following [Bhavani et al., 2021]. However, in real clinical practice, the withdrawal of a ventilator from one patient to save another raises ethical issues and has not reached a consensus (e.g., ranging from no mechanism in the Maryland protocol to an explicit SOFA-based approach in the New York protocol). Therefore, we also include the results without this constraint in Appendix A.5 1 to provide a comprehensive picture across the spectrum, considering both extremes where withdrawal is either considered or not at all.
Therefore, the action space is shrunk to A = {a ∈ {0, 1}N : ∑Ni=1 ai ≤ C and ai = 1 if Ii = 1, ∀i = 1, 2, · · · , N}.
3.3 TransitionModel
For ease of notation, we denote the three special conditions Survived, Dead, and Vacant as 1,-1, 0 ∈ Rk respectively. In the case without fairness consideration, given current state s = [x1, x2, · · · , xN, I1, I2, · · · , IN] and action a = [a1, a2, · · · , aN], it will transit to the next state s′ = [x′1 , x′2 , · · · , x′N , I ′1 , I ′2 , · · · , I ′N ] in the following coordinatewise way:
- If xi ̸= 0, 1,-1, then the patient will transit to Dead condition if not ventilated:
where pon (x′i |xi) denotes the probability of a patient transiting from medical condition xi to x′i given ventilation. The ventilation status is naively transited P vent i (I ′ i |s, a) = 1 if I ′ i = ai and 0 otherwise. We did not use computational methods to simulate pon (x′i |xi), as the progression of patients' conditions is highdimensional and difficult to model. Instead, we only used real clinical trajectories by sampling from realworld clinical databases.
Following existing clinical literature (e.g., [Bhavani et al., 2021]), we assume that patients who needed ventilators but did not receive one will die. Thus, there will be no patients waiting for a ventilator, as the inability to receive ventilation will result in their immediate deceased and removal from the dataset. However, such an assumption might be over-pessimistic. Therefore, in Appendix A.6, we also explore scenarios where patients not being allocated ventilators does not lead to immediate fatalities, which validates the broader applicability of our proposed methods.
- If xi = 0, 1 or -1, the action does not influence the transition dynamic:
1 https://arxiv.org/pdf/2309.08560
where ξ(·) denotes the distribution of the initial medical condition of a patient when admitted to the critical care units, and qi(s) denotes the probability of a new incoming patient staying in bed i. Note qi(s) depends on how new patients are distributed to empty beds. It satisfies qi(s) = 0 if the bed i is already occupied, and ∑Ni=1 qi(s) = E ∼ Poisson(Λ) assuming the number of incoming patients E obeys an Poisson distribution with parameter Λ. The ventilation status does not matter at this point, we can set P vent i (I ′ i |s, a) = 1 if I ′ i = 0 and 0 otherwise.
Given above discussion for transition dynamics of each individual patients/bed, the overall transition probability can be written as
We further consider the progress of the number of cumulative patients and ventilated patients of each ethnic group, whose deterministic transitions are naive by their definitions.
3.4 Reward
The reward function consists of the following three parts:
- Terminal condition Rt: If a patient is discharged alive after being on a ventilator, a positive reward of 1 is given. If a patient requires a ventilator but is not able to receive one, or dies after being on a ventilator, a penalty of -1 is given: Rt(s, a) = ∑Ni=1 1[xi = 1]-∑Ni=1 1[xi = -1].
- Ventilation cost Rv: if a ventilator is used, it occurs a small negative reward:Rv(s, a) = ∑Ni=1 ai.
- Fairness penalty Rf : in the case with fairness consideration, we consider the cumulative total and ventilated patients of different ethnoracial groups. We expect the distribution of ventilators is equitable in terms of the proportion of ventilated patients of all ethnoracial groups. Therefore, a penalty of KLdivergence between the frequency distributions of incoming patients of different ethnoracial groups Dn d∼ [nB, nW, nA, nH]/(nB + nW + nA + nH) and ventilated patients of different ethnoracial groups Dm d∼ [mB, mW , mA, mH ]/(mB +mW +mA +mH) is considered: Rf (s, a) = KL (Dn∥Dm).
Thus, the reward function is given by
where the parameter λ ≥ 0 balances the trade-off between ventilation effectiveness and fairness. In the case without fairness consideration, we set λ = 0. µ is a small scalar that controls ventilation costs and can be selected through parameter fine-tuning or clinical expertise.
4 Method
In our formulation, due to the resource constraints imposed through the restricted action sets and the fairness requirements via reward penalties, the interaction effects among the patients need to be considered. However, modeling all patients jointly poses computational and memory challenges due to the combinatorial nature of the action space. Addressing such a formulation necessitates a Q network with dimensions proportional to the size of the state space |S| and action space |A|, resulting in a complexity up to O(N ×2N ), where N represents the ICU bed capacity. This complexity makes it impractical to naively construct and train such a Q network, given the challenges in collecting a sufficient number of data points. In practical terms, the intensive care units of health systems typically have hundreds of beds (N ≥ 100), making the computational demands and data requirements for training such a network unattainable. Also, naively concatenating all patients' state vectors introduces an order among patients, which may cause the model to learn artificial factors on that order and potentially bias the model.
To circumvent the computational intractability without losing the consideration of the interaction effects among patients, we therefore propose Transformer-based Q-network parametrization, which inherits the classical Q-learning framework with new parametrization and greedy action selection tailored to our problem structure. In our formulation, the transition of states is partially decomposable because a single patient's clinical conditions depend only on their preceding clinical conditions and ventilation status. Therefore, we can reshape the state from a one-dimensional long vector to a two-dimensional matrix, with the i-th row as [xi, Ii] for patient i. In case the fairness features nk,mk are also considered, we can replicate them N times and append them to the end of each row. The Q-network is parametrized as Tθ : Rdim(S) → RN×2 , whose input is the reshaped state matrix. The i-th row of the output Tθ(s)i ∈ R2 corresponds to the Q-value contributed by the i-th patient given the current state s and the action ai on the i-th patient. We adopt an additive form of the joint Q-value, which estimates the trade-off between effectiveness and fairness when allocating under the constraints and considering the clinical conditions of all patients: Q(s, a) = ∑Ni=1 Tθ(s)i,ai . We leverage the Transformer architecture [Vaswani et al., 2017] for Tθ. Each row in the reshaped s are considered as an input patient token. As our input to the model is essentially an orderless set of patients' conditions with indefinite size, Transformers are a natural fit for our problem because Transformers without positional encodings are permutationally-invariant and can handle inputs with arbitrary sizes. Each Transformer layer is composed of a feed-forward layer and a multi-head attention layer. The feed-forward layer acts independently on each element of the input as a powerful feature extractor, while the attention layer is able to capture the interaction effects between all the elements. This quadratic complexity of Transformer architecture also results in a significant reduction in the network's complexity, decreasing it fromO(N×2N ) to a more manageable O(N 2 ). We also provide robust empirical results to demonstrate the effectiveness and advantages of our proposed transformer-based parametrization compared to the classical deep Q-network in Appendix A.4.
In this parametrization, the greedy action shall be searched within the valid action space A to accommodate the withdrawal and capacity constraints: πθ(a|s) : a∗ = argmaxa∈A ∑Ni=1 Tθ(s)i,ai . Under our parametrization and the additive form of the Q-value, this constrained greedy search can be efficiently solved by first allocating ventilators to those who have already been allocated (withdrawal constraint), where a∗i = 1 ⇔ Ii = 1. Subsequently, the remaining (C - ∑Ni=1 Ii) ventilators are allocated to the newly admitted patients for whom the ventilation improvement di = Tθ(s)i,1 - Tθ(s)i,0 ranks at top-(C - ∑Ni=1 Ii) among all their competitors (capacity constraints).
We also develop a simulator, Simu(X;C,Λ), constructed from real-world clinical trajectories to create the replay buffer for training the proposed model. This simulator maintains the clinical trajectory of each patient while randomizing their relative admission order. X is a set of clinical trajectories from all patients in the training cohort, with each trajectory being of various lengths covering all the clinical conditions of a patient in the critical care unit. At each time step in the simulator, we sample the initial conditions of E patients from X without replacement. E is determined by a Poisson distribution with parameter Λ, inferred from the distribution of ventilator requests in the training cohort. We apply a protocol Π to allocate the available C ventilators when the sum of existing patients and newly admitted E patients exceeds the capacity C. Patients who are not allocated ventilators or those who are discharged (either alive or deceased) are removed from the ongoing simulator and returned to the sampling pool. Patients who are allocated ventilators progress to the next time step of their own trajectory based on the transition function pon (x′i |xi). With this simulator setup, we can generate MDP tuples of indefinite length.
We combine the Transformer q-network parametrization with Double-DQN (TxDDQN) [Van Hasselt et al., 2016], a variant to the original DQN [Mnih et al., 2013] capable of to reduce overestimation. We summarize our proposed model and simulator in Algorithm 1.
5 Experiments
5.1 Dataset
The dataset is sourced from Northwestern Medicine Enterprise Data Warehouse (NMEDW), including electronic health records, pathology data from multiple real-world hospitals and research laboratories. We collected 11,773 ICU admissions that have been allocated mechanical ventilators between March 15, 2020 and January 15, 2023. We filtered the patients with age between 18 and 95 for consideration. We removed admissions with a ventilator allocation duration exceeding 30 days to eliminate anomalies in the data. We extracted 38 features for each admission, including SOFA components, vital signs, demographics, comorbidities (see Appendix A.1 for the list of features and their statistics).
We split our data into 3 splits, 5,455 admissions between March 15, 2020 and July 14, 2021 were used as training data; 1,047 admissions between July 15, 2021 and October 14 2021 were used as validation data on which we selected the best hyper-parameters for testing; 5,271 admissions between October 15, 2021 and January 15, 2023 were used as test data. The patient distribution of different races and the ventilator demands on each day are shown in Appendix A.1. We assume that the original dataset obtained from health systems reflects Algorithm 1 Transformer-based Double Deep Q Network Input: Simu(X;C,Λ), discount factor γ, learning rate α, batch size |B|, loss function Lc,network update frequency h, network update parameter τ
Initialize: Primary network Tθ0 ; Target network Tθ′ , θ′ ← θ0; Allocation protocol Π ← πθ0 ; D ← Φ; s(0) by sampling initial medical conditions of Pois(Λ) patients from X for e = 0 to E ▷ Training loop in epochs
for t = 0 to T - 1 ▷ Construct a ring replay buffer a ∼ πθe (s) ▷ πθ(a|s) : a∗ = argmaxa∈A ∑Ni=1 Tθ(s)i,ai s′ ∼ P(s, a) ▷ Eq. (1) for P(s, a) D ← D ∪ {(s, a, s′ , R(s, a)} ▷ Eq. (2) for R(s, a) θe,0 ← θe for g = 0 to G - 1 ▷ Gradient steps Sample mini-batch B ⊂ D ▷ B = {(s, a, s′ , r}|B| for i = 0 to N ▷ Search next action a′∗ di = (Tθe,g (s′ )i,1 -Tθe,g (s′ )i,0) ▷ Vent. improv. if I ′ i = 1 then a′i ← 1 ▷ Withdrawal constraint elif di ranks top- (C - |I ′ |) in {di | I ′ i = 0}then a′i ← 1 ▷ Capacity constraint else a′i ← 0 θe,g+1 ← θe,g-α·∇θLc[∑Ni=1 Tθe,g (s)i,ai , R(s, a)+ γ · ∑Ni=1 Tθ′ (s′ )i,a′i ] ▷ Policy update if g mod h = 0 then θ′ ← τ · θe,g+1 + (1 - τ) · θ′ θe ← θe,Ga scenario where there was an abundant supply of ventilators available. We aim to investigate the effectiveness of various protocols in mitigating excess deaths in ventilator scarcity.
This setup differed from conventional RL settings, which are trained and evaluated solely on a simulator. We had separate validation and testing sets. This design allowed us to compare the proposed method with existing protocols in realworld hospital operational settings, enhancing the effectiveness and generalizability of our model. Additionally, ventilator demands may fluctuate due to seasonality and outbreaks. A test set spanning a whole year can assess our method's vulnerability to these seasonal request surges.
5.2 Baseline Protocols
Our proposed method was compared with the following existing triage protocols: Lottery: Ventilators are randomly assigned to patients who are in need. Youngest First: The highest priority is given to the youngest patients. SOFA: Patients' prioritization is discretized into three levels (0-7: high, 8-11: medium, and 11+: low) with the lottery serving as the tiebreaker. Multiprinciple (MP): Each patient is assigned a priority point based on their SOFA score (0-8: 1, 9-11: 2, 12-14: 3, 14+: 4). Patients with severe comorbidities receive an additional 3 points. In case of ties, priority is given to patients in a younger age group (Age groups: 0-49, 50-69, 70-84, and 85+). If ties still exist, a lottery is conducted to determine the final allocation. Decision Tree (DT): GrandCl´ement et al. [Grand-Cl´ement et al., 2021] introduced a data-driven decision-tree-based approach for optimizing ventilator allocation. Their protocol factors in the BMI, age, and SOFA score, classifying patients into two priority levels. Admission time is the tie-breaker within the same priority level.
| Survival | Fairness | Allocation Rates | |||||
|---|---|---|---|---|---|---|---|
| Survival, % | DPR, % | Overall, % | Asian, % | Black, % | Hispanic, % | White, % | |
| Lottery SOFA DT | 75.17 ±0.45 | 96.89 ±1.55 86.39 ±0.27 92.37 ±1.01 94.35 ±0.01 | 75.60 ±0.28 75.65 77.92 75.81 78.34 | 74.95 ±1.81 75.59 75.06 79.59 77.91 | 75.65 ±1.10 81.73 ±0.31 73.58 ±0.77 75.14 ±0.01 74.33 ±0.66 | 76.08 ±0.90 84.44 ±0.30 78.66 ±1.24 77.34 ±0.00 81.96 ±0.56 | 75.68 ±0.33 72.94 79.10 75.58 |
| Youngest | 77.24 ±0.07 | ±0.09 | ±0.50 | ±0.12 | |||
| 80.88 ±0.32 | ±0.25 | ±1.44 | ±0.45 | ||||
| 76.16 ±0.01 | ±0.01 | ±0.00 | ±0.00 | ||||
| MP | 81.99 ±0.14 | 90.68 ±0.95 | ±0.20 | ±1.48 | 78.81 ±0.34 | ||
| TxDDQN | 84.76 ±0.24 | 86.91 ±3.45 | 81.80 ±0.26 | 78.03 ±0.99 | 72.48 ±0.74 | 81.71 ±0.44 | 84.45 ±0.22 |
| TxDDQN-fair-off | 85.29 ±0.18 | 95.27 ±1.42 | 81.96 ±0.15 | 80.50 ±2.23 | 80.07 ±1.98 | 81.44 ±1.05 | 82.70 ±0.34 |
| TxDDQN-fair | 85.41 ±0.23 | 95.24 ±1.65 | 81.90 ±0.24 | 80.01 ±1.79 | 79.95 ±1.05 | 81.26 ±1.24 | 82.80 ±0.42 |
5.3 Off-policy and offline training
The maximum daily demand for ventilators in the validation and testing sets is 85. Therefore, we trained 85 capacityspecific protocol models C = 1, 2, · · · , 85. Ventilator capacity is normalized from [0, 85] to [0%, 100%]. We used Λ = 12 because the number of daily newly admitted patients to the critical care units in our dataset follows a Poisson distribution with Λ = 12. Our simulator supports both offpolicy and offline RL training settings [Levine et al., 2020]. In the off-policy RL setting, we iteratively update Π with πθ when constructing the replay buffer. We refer to the offpolicy trained model without and with fairness consideration as TxDDQN and TxDDQN-fair. In the offline setting, we use existing heuristic-based protocol, MP, as Π to create a large training set and do not update the training data during the training process. This offline training process mimics early-stage health crisis operations where resources are allocated using existing protocols, and improvements are sought thereafter. We refer the offline trained model with fairness consideration as TxDDQN-fair-off. Our experiments were conducted on firewall-protected servers. The training time for each capacity-specific model was less than 30 minutes using a single GPU. For hyper-parameter selections and the survivalfairness Pareto frontier, please see Appendix A.2.
5.4 Evaluation
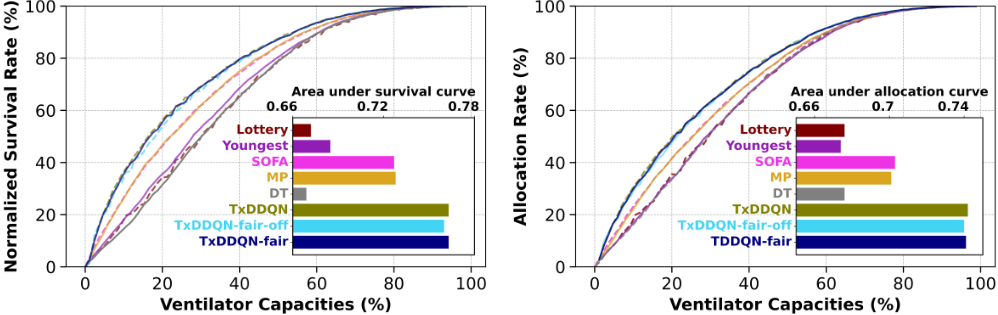
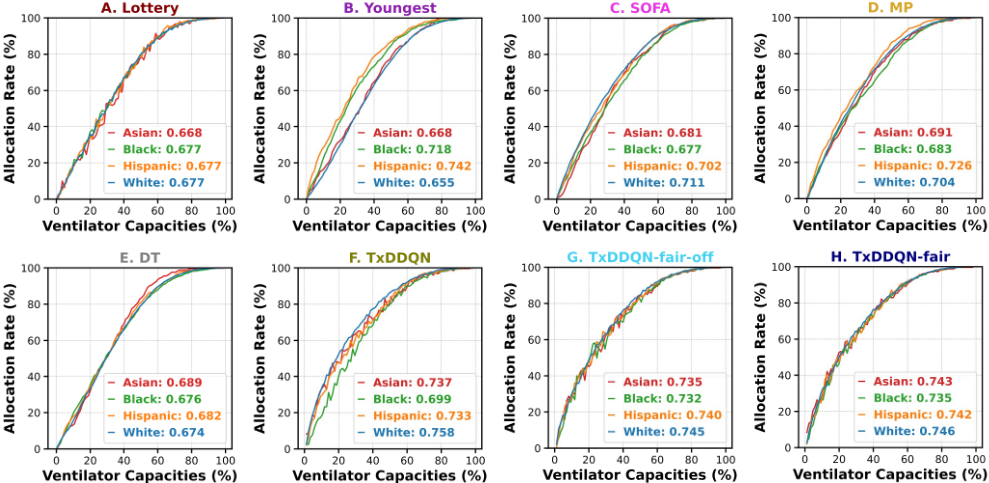
We evaluated the performance of our proposed protocol based on normalized survival rates, with the survival number at no shortage in ventilators as 100% and no patients alive when no ventilator is available as 0%. Fairness was quantified by comparing the allocation rates across four ethnoracial groups. The allocation rate was calculated by dividing the total number of ventilators allocated by the sum of the ventilators requested. The demographic parity ratio (DPR) [Bird et al., 2020] served as the group metric of fairness, and it is defined as the ratio between the smallest and largest group-level allocation rate. A DPR value close to 1 signifies an equitable allocation, indicating a non-discriminatory distribution among the different groups. Additionally, to gain insights into the impact of protocols under varying shortage levels, we visualized the survival-capacity curve (SCC) and allocationcapacity curve (ACC). The Area Under the Survival-Capacity Curve (AUSCC) serves as an indicator of the overall performance in terms of life-saving abilities under different levels of ventilator shortage. Similarly, the Area Under the Allocation-Capacity Curve (AUACC) reflects the overall performance of ventilator utilization rates under varying levels of shortage.
5.5 Results
Our findings regarding the survival rates for different triage protocols under various levels of ventilator shortage are illustrated in Figure 2. Across all triage protocols, higher ventilator capacities are associated with increased allocation rates, thereby resulting in saving more lives. In the left Panel of Figure 2, our proposed TxDDQN models exhibit higher AUSCC compared to all other baseline protocols, demonstrating the superiority of our models in terms of life-saving efficacy. Likewise, in the right Panel, TxDDQN models also demonstrate higher AUACC compared to other baselines, indicating their superiority in terms of ventilator utilization.
Figure 3 showcases the allocation-capacity curves for different ethnoracial groups and triage protocols in Panels A through H. Only Lottery, TxDDQN-fair and TxDDQN-fairoff model exhibit minimal disparities, but TxDDQN-fair and TxDDQN-fair-off surpasses Lottery in terms of allocation rates and life-saving efficacy. Conversely, all other triage protocols display a preference for specific ethnoracial groups. For example, Youngest and MP favor Hispanic, while SOFA and TxDDQN favor White.
We conducted a detailed analysis in Table 1 under the scenario where approximately 50% of ventilators are unavailable. Our results show that TxDDQN-fair achieves the highest survival rate and allocation rate among the triage protocols. It ranks second in terms of DPR, following closely behind the Lottery protocol. These findings confirm the effectiveness of our TxDDQN-fair approach in improving both survival rates and fairness simultaneously. Importantly, the inclusion of fairness rewards does not compromise its lifesaving capabilities compared to TxDDQN. We also did not observe differences between TxDDQN-fair and TxDDQNfair-off in their life-saving abilities and fairness. This confirms that our proposed methods are adaptable to both offline and off-policy training, and provide the foundation for safe deployment in the early stages of health crises. Our proposed model also demonstrates enhanced fairness and life-saving outcomes in two additional settings: i) where withdrawal constraint is removed (Appendix A.5), and ii) the shortage of ventilators does not lead to immediate deaths (Appendix A.6). We provide ablation studies in Appendix A.3.
6 Summary
In this study, we formulated fair health care resource allocation as a multi-objective deep reinforcement learning problem. We developed a transformer-based deep Q network to integrate individual patient disease progression and interaction effects among patients to optimize for an efficient and fair allocation policy. Our proposed model outperformed existing protocols used by different states in the U.S., by saving more lives and achieving a more equitable allocation of health resources. We refer the reader to Appendix A.7 for the limitations and future directions of this study.
Ethical Statement
The study used real patient data, which underwent Institutional Review Board (IRB) approval to ensure compliance with ethical research principles and regulatory requirements. All experiments and data processing were performed on HIPAA-compliant internal servers, ensuring the confidentiality and security of sensitive health information. The deidentified dataset used in this study will be available as a subset of a consortium-level federated dataset. Throughout the study, efforts were made to minimize bias and ensure that allocation protocols align with established ethical frameworks, promoting fairness, equity, and maximization of benefits in the allocation of health resources.
Contribution Statement
Authors Y.Li, C.M., K.H., H.W., and Z.Y. contributed equally to this work and are designated as co-first authors (marked with an asterisk * in the author list). Authors M.W. and Y.Luo, who serve as PhD advisors to the co-first authors, jointly and equally supervised this work and are recognized as co-senior authors (marked with a dagger †in the author list).
@inproceedings{ijcai2025p1088,
  title     = {Deep Reinforcement Learning for Efficient and Fair Allocation of Healthcare Resources},
  author    = {Li, Yikuan and Mao, Chengsheng and Huang, Kaixuan and Wang, Hanyin and Yu, Zheng and Wang, Mengdi and Luo, Yuan},
  booktitle = {Proceedings of the Thirty-Fourth International Joint Conference on
               Artificial Intelligence, {IJCAI-25}},
  publisher = {International Joint Conferences on Artificial Intelligence Organization},
  editor    = {James Kwok},
  pages     = {9790--9798},
  year      = {2025},
  month     = {8},
  note      = {AI and Social Good},
  doi       = {10.24963/ijcai.2025/1088},
  url       = {https://doi.org/10.24963/ijcai.2025/1088},
}
TY - CPAPER TI - Deep Reinforcement Learning for Efficient and Fair Allocation of Healthcare Resources AU - Li, Yikuan AU - Mao, Chengsheng AU - Huang, Kaixuan AU - Wang, Hanyin AU - Yu, Zheng AU - Wang, Mengdi AU - Luo, Yuan T2 - Proceedings of the Thirty-Fourth International Joint Conference on Artificial Intelligence, IJCAI-25 PB - International Joint Conferences on Artificial Intelligence Organization PY - 2025 SP - 9790 EP - 9798 DO - 10.24963/ijcai.2025/1088 UR - https://doi.org/10.24963/ijcai.2025/1088 ER -Copied
Machine-readable versions of this paper, for tools and AI agents:





